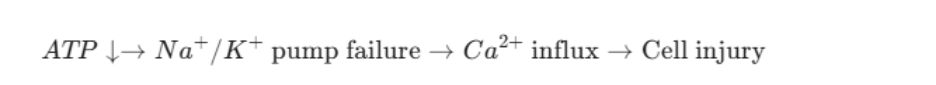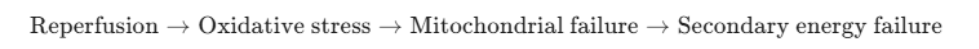TORCH Profile by Dr. Anand Bhatia

TORCH Profile Explained: What Every Pediatric Resident Must Know 

When it comes to neonatal infections and congenital anomalies, few topics are as high-yield—and frequently tested—as the TORCH profile. Whether you’re preparing for exams or managing real clinical cases, understanding this panel is absolutely essential. 

But here’s the problem: most residents memorize it… without truly understanding it. 

Let’s fix that. 

What is the TORCH Profile? 

The TORCH profile is a group of infections that can be transmitted from mother to fetus, often leading to serious complications. 

TORCH stands for: 
  • T – Toxoplasmosis  
  • O – Others (Syphilis, Varicella, Parvovirus B19, HIV, Hepatitis B)  
  • R – Rubella  
  • C – Cytomegalovirus (CMV)  
  • H – Herpes Simplex Virus (HSV)  

These infections are especially important because they can silently affect fetal development and present later with severe manifestations. 
 
Also Read: Turner vs Noonan Syndrome: The Quick Clinical Differentiation done By Dr. Anand Bhatia Every Pediatrics Resident Should Know  

Why Should Pediatric Residents Care? 

Because this is not just theory—it’s something you’ll face in: 

  • Neonatal ICU postings  
  • Developmental delay cases  
  • Congenital anomaly evaluations  
  • Exam MCQs and case scenarios  

Missing a TORCH infection can mean missing a critical diagnosis. 

When Should You Suspect TORCH Infections? 

Think of TORCH when you see: 

  • Intrauterine growth restriction (IUGR)  
  • Microcephaly or hydrocephalus  
  • Hepatosplenomegaly  
  • Jaundice at birth  
  • Seizures in neonates  
  • Chorioretinitis or cataracts  
  • Intracranial calcifications  

👉 These are classic red flags you should never ignore. 

Trimester-Wise Impact: Why Timing Matters 

One of the most important (and often overlooked) aspects is when the infection occurs during pregnancy. 

  • First trimester → Severe congenital anomalies  
  • Second trimester → Structural defects + growth issues  
  • Third trimester → Less severe, but still clinically significant infections  

Understanding this helps you correlate history + presentation in exams and real cases. 

High-Yield Highlights You Shouldn’t Miss 

Here are some exam-focused pearls: 

  • Toxoplasmosis → Intracranial calcifications + chorioretinitis  
  • Rubella → Cataract + PDA + deafness (classic triad)  
  • CMV → Most common congenital infection; periventricular calcifications  
  • HSV → Severe neonatal sepsis-like presentation  
  • Syphilis (Others) → Snuffles, rash, and bone involvement  

These are frequently tested—don’t just memorize, understand the patterns. 

Common Mistakes Residents Make 

Let’s be honest—most mistakes happen because of: 

  • Treating TORCH as a single test, not a clinical concept  
  • Ignoring maternal history  
  • Not correlating symptoms with timing  
  • Relying only on reports instead of clinical reasoning  

Avoid these, and you’ll already be ahead of most. 

How to Approach TORCH in Clinical Practice?

A smart approach includes: 

  1. Detailed maternal history (fever, rash, infections during pregnancy)  
  2. Focused neonatal examination  
  3. Targeted investigations (not blind testing)  
  4. Correlation with imaging findings  

👉 Always think clinically first, then confirm with tests. 

Final Takeaway 

The TORCH profile isn’t just a list—it’s a framework for thinking. 

Mastering it will not only boost your exam performance but also make you more confident in managing real pediatric cases. 

Want to Go Beyond Just the Basics? 

What you just read is only a glimpse. 

At Conceptual Pediatrics, we don’t just teach—you learn how to think like a pediatrician. From high-yield concepts to real clinical correlations, every session is designed to make your residency smoother and smarter. 

👉 Download the eConceptual App today 
👉 Explore Conceptual Pediatrics and make it your ultimate residency partner 

Whether you choose the Solo plan or study smarter with the Buddy plan, you’ll unlock a whole new level of clarity. 

Don’t just study pediatrics—master it. 

Understanding the Phases of HIE by Prof. NB Mathur

Understanding the Phases of HIE: Why the First 6 Hours Are Everything 

In the NICU, time is often our most precious resource. Few conditions prove this more than Hypoxic Ischemic Encephalopathy (HIE). When a newborn is deprived of oxygen around the time of birth, the brain injury isn’t a single, static event. Instead, it’s an evolving process that unfolds over hours and days. 

This is why neonatologists are so hyper-focused on the first six hours of life. In a recent teaching session, Prof. NB Mathur broke down the phases of HIE in a way that moves past the textbooks and into real-world clinical practice. Once you see the timeline, the “why” behind our treatments becomes crystal clear.  
 
Watch Session:  Phases of Hypoxic Ischemic Encephalopathy (HIE): Pathophysiology & Clinical Window | Prof. NB Mathur 

1. Primary Energy Failure: The Initial Hit 

This phase happens within minutes of the hypoxic event. When oxygen and glucose levels plummet, the brain’s “power plants” fail. 

Without enough ATP (energy), the cellular pumps that maintain balance stop working. Sodium and calcium flood into the cells, causing them to swell. The chemical chain reaction looks something like this: 

As this is happening, several fires start at once: lactate levels rise, glutamate is released, and oxidative stress begins. While some neurons die immediately, many others are “stunned”—damaged but still salvageable if we act fast. 

2. The Latent Phase: Our “Golden Window” 

After the initial crisis, there is often a deceptive period of calm called the Latent Phase, usually lasting between 1 to 6 hours. 

During this time: 

  • Resuscitation has stabilized the baby’s circulation. 
  • Oxygen supply has partially returned. 
  • ATP production temporarily ticks back up. 

Clinically, this phase can be a “trap.” The baby might look relatively stable, leading to a false sense of security. But under the surface, the injury is quietly simmering. Calcium overload and mitochondrial dysfunction are still active. 

This is the most critical window in HIE management. Therapeutic hypothermia (cooling) is most effective during these first six hours. For residents, remembering this window is the difference between reactive and proactive care. 

3. Secondary Energy Failure: The Second Wave 

Starting around the 6-hour mark and lasting up to 48 hours, the Secondary Phase (or reperfusion injury) begins. 

It sounds counterintuitive—why does the brain get worse once blood flow returns? 

Even with oxygen available, the damaged mitochondria can’t use it. Inflammatory “alarms” (cytokines like TNF-alpha and IL-6) go off, further damaging neurons and the brain’s white matter. This is when the most significant, permanent neuronal loss often occurs. 
 

4. The Tertiary Phase: The Long Road to Recovery 

The Tertiary Phase begins weeks after the initial event and can last for months. This is a complex period where the brain is simultaneously dealing with chronic inflammation and trying to repair itself. 

While the damage may continue, the brain also shows incredible plasticity. Through neurogenesis and remodeling, the brain attempts to rewire. This is why long-term developmental follow-up is non-negotiable; we aren’t just treating a baby in the NICU, we are managing their potential for the rest of their life. 

Why This Matters for Residents?

HIE can feel like an overwhelming mountain of pathways and terminology. But when you look at it as a timeline, it becomes a clinical map. 

You start to see why the “Golden Six Hours” isn’t just a catchphrase—it’s the only time we have to truly change the trajectory of the injury. When you understand these phases, HIE stops being a topic you memorize for rounds and starts being something you can actually visualize at the bedside. 

Want to get deeper into clinical pediatrics? 

If you found this helpful, the Conceptual Pediatrics App offers many more high-yield sessions designed specifically for residents. From NICU protocols to emergency cases, we focus on simplifying the complex so you can focus on your patients. 

Share